

A single testosterone result is not a diagnosis. Learn how clinicians interpret male hormone levels using physical symptoms, repeat testing and health context.





A clinical testosterone result is a quantitative measurement of hormone concentration in the blood at a precise moment in time. It represents a single biological data point rather than a complete medical condition. Medical professionals use this isolated number as one piece of evidence in a broader diagnostic process. A standalone laboratory value cannot confirm a hormone deficiency without additional context.
This article is intended strictly for informational purposes and does not constitute medical advice. Readers should always consult a qualified healthcare professional regarding personal health concerns. The information provided here cannot replace a proper clinical evaluation or a formal medical diagnosis. Never start or adjust medical treatments based on generalized educational content.
Medical guidelines offer different numerical thresholds to help clinicians evaluate male hormones. The American Urological Association (AUA) uses a total testosterone measurement below 300 ng/dL as a reasonable cutoff to support a diagnosis. This figure must be paired with compatible symptoms and confirmed through repeat morning testing. A single low reading under this threshold does not automatically equal a hypogonadism diagnosis.
Other professional bodies rely on slightly different numerical reference points for their evaluations. One secondary comparison reports an Endocrine Society value of 264 ng/dL. This specific lower reference limit is derived from CDC-harmonized measurements in healthy, non-obese men between the ages of 19 and 39. Patients should not view these differing figures as interchangeable diagnostic standards.
It is important to note that these specific guideline comparisons often reach the public through secondary medical summaries. Primary guideline texts contain extensive technical nuance regarding how these thresholds apply across different age brackets. A secondary comparison might present these values side by side, but clinical practitioners apply them with much more context. Readers should discuss these specific cutoffs directly with a medical professional rather than diagnosing themselves online.
Guidelines use these different numerical approaches to support overall clinical judgment. A doctor will review a complete hormone panel to understand the patient's baseline. Total testosterone measures all the hormone circulating in the bloodstream at that moment. Free testosterone represents the unattached portion that is readily available for the body to use.
A summary of Endocrine Society guidance notes that free testosterone testing can be highly clarifying. Clinicians often consider this measurement when a total testosterone result sits near the lower limit of normal. Borderline results frequently require this secondary level of testing to provide a clear picture. This ensures that the diagnostic process remains focused on the patient.
Conditions that alter sex hormone-binding globulin (SHBG) can make total testosterone harder to interpret. SHBG is a specialized protein that attaches to sex hormones in the blood. When SHBG levels fluctuate, the amount of free testosterone available to the body changes accordingly. This is why a normal total testosterone result might still accompany recognizable physical symptoms.
Checking free testosterone helps clarify the overall clinical picture when this discordance occurs. This secondary assessment is not a universal requirement for every single patient. It is utilized strategically when the initial laboratory data does not match the clinical presentation. A comprehensive evaluation relies on understanding these binding proteins and their downstream effects.
Physicians must weigh these variables carefully before making any formal medical determinations. The presence of elevated or depressed SHBG can obscure the true hormonal reality. Proper clinical interpretation requires looking past the top-line number to understand the underlying biology. This detailed approach separates rigorous medical practice from superficial laboratory analysis.
Adult men may experience noticeable physical changes when hormone levels fluctuate outside the normal range. The Endocrine Society diagnostic framework requires compatible symptoms or signs alongside testosterone that is unequivocally and consistently low. Clinicians look for specific complaints during a comprehensive patient history and physical examination. They do not treat a testosterone number in isolation.
Sexual symptoms are among the most commonly discussed signs in medical literature. Reduced sexual desire is frequently reported by men seeking a hormone evaluation. Patients also commonly report experiencing fewer spontaneous or morning erections. Research notes that these symptoms require careful clinical interpretation rather than serving as a standalone diagnosis.
It is crucial to understand that these physical signs are not strictly specific to testosterone deficiency. Many other health conditions can produce similar clinical complaints in adult men. A physician must carefully evaluate whether these physical changes align logically with the laboratory results. This comprehensive approach helps prevent misdiagnosis and avoids inappropriate medical treatments.
To navigate this diagnostic complexity, patients can prepare by noting the onset of their symptoms. Documenting these physical changes over time provides highly valuable context for a medical professional. If a man wants to prepare for a testosterone test and interpret the results, he should share this specific symptom history with his doctor. Clinical context is what gives laboratory numbers their actual medical meaning.
Sometimes a patient will present with classic symptoms but return a completely normal hormone panel. Conversely, a man might have a lower testosterone reading without experiencing any negative physical changes. This mismatch is exactly why medical guidelines insist on pairing symptoms with laboratory data. Treating numbers on a chart without addressing the physical reality is poor practice.
When interpreting low testosterone symptoms, doctors look for persistent patterns rather than isolated events. Fatigue and mood changes might be related to hormones, but they could also stem from poor sleep. The diagnostic framework exists to rule out these overlapping conditions methodically. A rigorous evaluation protects patients from jumping to incorrect conclusions about their health.
Clinicians understand that symptom severity does not always correlate perfectly with laboratory values. Two men with identical blood panels might experience entirely different daily realities. This individual variance highlights the limitations of relying purely on reference ranges. The patient's reported lived experience remains a central pillar of the diagnostic process.
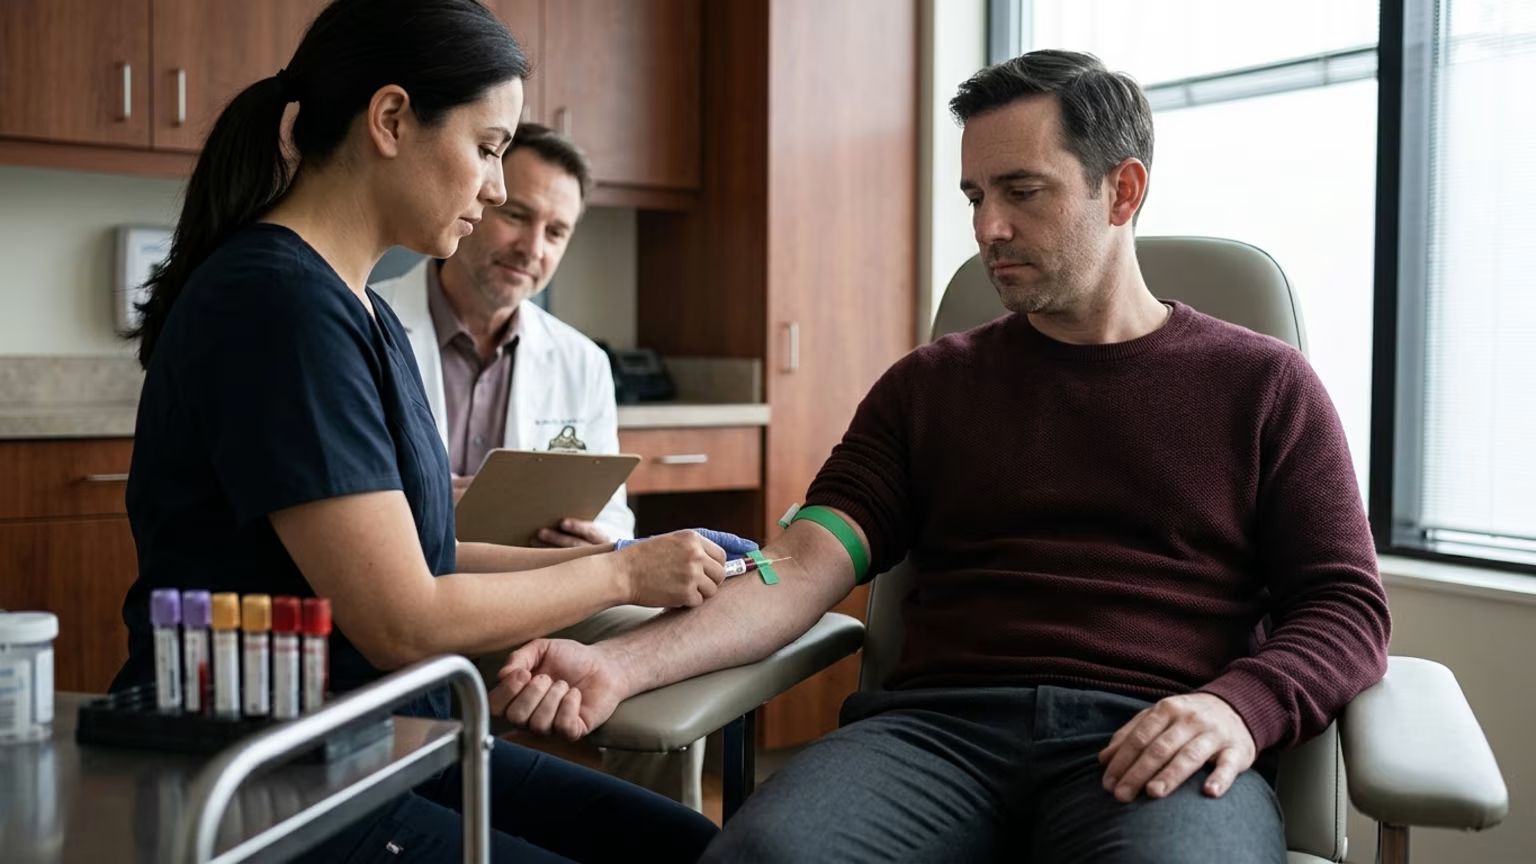
A testosterone measurement is highly sensitive to the exact conditions under which the blood is drawn. The AUA approach calls for two early-morning total testosterone measurements taken on separate occasions. Hormone levels naturally peak in the early hours of the day for most adult men. Taking a blood test later in the afternoon can yield an artificially low result.
Fasting status is another variable where major medical guidelines differ slightly. A secondary comparison describes the Endocrine Society as specifying a fasting morning test. Conversely, the AUA approach is reported to require early-morning testing without a strict fasting requirement. The European Association of Urology specifies early-morning fasting testing specifically for erectile dysfunction assessments.
Because these recommendations vary, a result taken at a different time of day is not comparable with a properly timed repeat measurement. Inconsistent testing conditions create confusing variations on a patient's laboratory report. Men should coordinate closely with their healthcare providers to ensure tests are administered correctly. Consistent testing protocols are absolutely essential for an accurate clinical diagnosis.
The available source comparison detailing these differing fasting rules comes from secondary health information pages. While these summaries are helpful for broad educational purposes, they do not capture every nuance of international clinical guidelines. A doctor will use the primary guideline text that best fits the patient's specific health profile. This reliance on primary medical texts ensures the highest standard of individualized patient care.
Physicians expect to see fluctuations between tests due to natural daily rhythms. Confirming an initially low reading with a second test helps eliminate statistical noise. This built-in redundancy prevents doctors from acting on a single anomalous result. The requirement for multiple readings underscores the cautious nature of evidence-based medicine.
Biological factors like obesity and diabetes heavily influence these hormone readings. These specific metabolic conditions are known contexts in which SHBG can be significantly altered. When SHBG is altered, total testosterone levels may not accurately reflect the patient's true hormonal status. This biological interference makes a straightforward diagnosis much more challenging for clinicians.
Altered SHBG levels can create a frustrating discordance between a patient's symptoms and their total testosterone score. Understanding how weight management influences low testosterone levels helps clarify why individual laboratory outcomes differ. When a patient has diabetes or is obese, clinicians often utilize free testosterone assessments. This targeted testing helps investigate the mismatch between physical symptoms and total hormone levels.
The numbers must be interpreted alongside the patient's existing metabolic health and lifestyle habits. A comprehensive evaluation looks at the entire biological system rather than a single hormonal pathway. Proper medical guidance ensures that these compounding health factors are properly addressed. This evidence-based approach provides a much clearer path forward for adult men.
Nutrition and overall metabolic health serve as the foundation for accurate hormonal interpretation. Clinicians must account for how a patient's weight history might skew the laboratory data. Ignoring these biological variables leads to an incomplete understanding of the patient's health. The most effective medical consultations integrate these lifestyle inputs directly into the diagnostic conversation.
Patients should ask their physician if their specific symptoms and health history match the initial blood test and whether a properly timed repeat measurement is medically necessary.
When men treat a single out-of-range laboratory value as definitive proof of a medical condition, they risk pursuing unnecessary treatments. Testostra steps in when readers face difficulty separating clinical evidence from marketing and social-media claims, providing the clear context needed to evaluate laboratory results safely. Read Resources
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.





Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra