

Understand low testosterone thresholds, repeat morning testing, and why weight and sleep belong in a broader clinical assessment.





Low testosterone is a laboratory finding in which the measured testosterone level falls below a clinical threshold used to assess possible hormone deficiency. It is not automatically a diagnosis of hypogonadism. The European Association of Urology (EAU) says late-onset hypogonadism requires compatible symptoms or signs together with consistently low morning testosterone.
This article is for informational purposes and is not medical advice. A qualified clinician should interpret personal symptoms and laboratory results. Decisions about further testing or testosterone therapy belong within that individual assessment.
The EAU guideline identifies 12 nmol/L (3.5 ng/mL) as a reliable diagnostic threshold in its summary of evidence. This number is used within an assessment for late-onset hypogonadism. It is not a universal treatment trigger.
It is more precise to describe this value as a lower diagnostic threshold than to call it the entire normal range. It does not supply an upper reference limit or establish an ideal testosterone level for every man. A threshold helps frame a clinical question rather than answering every question about hormonal health.
The biological finding is a low measured testosterone concentration. The clinical question is whether that finding is consistent and accompanies compatible symptoms or signs. Neither the concentration alone nor the presence of symptoms alone meets the EAU's combined diagnostic approach.
The terminology on a report also deserves attention. Background on reading total and free testosterone measurements can help prepare the questions that arise when reviewing hormone results with a clinician.
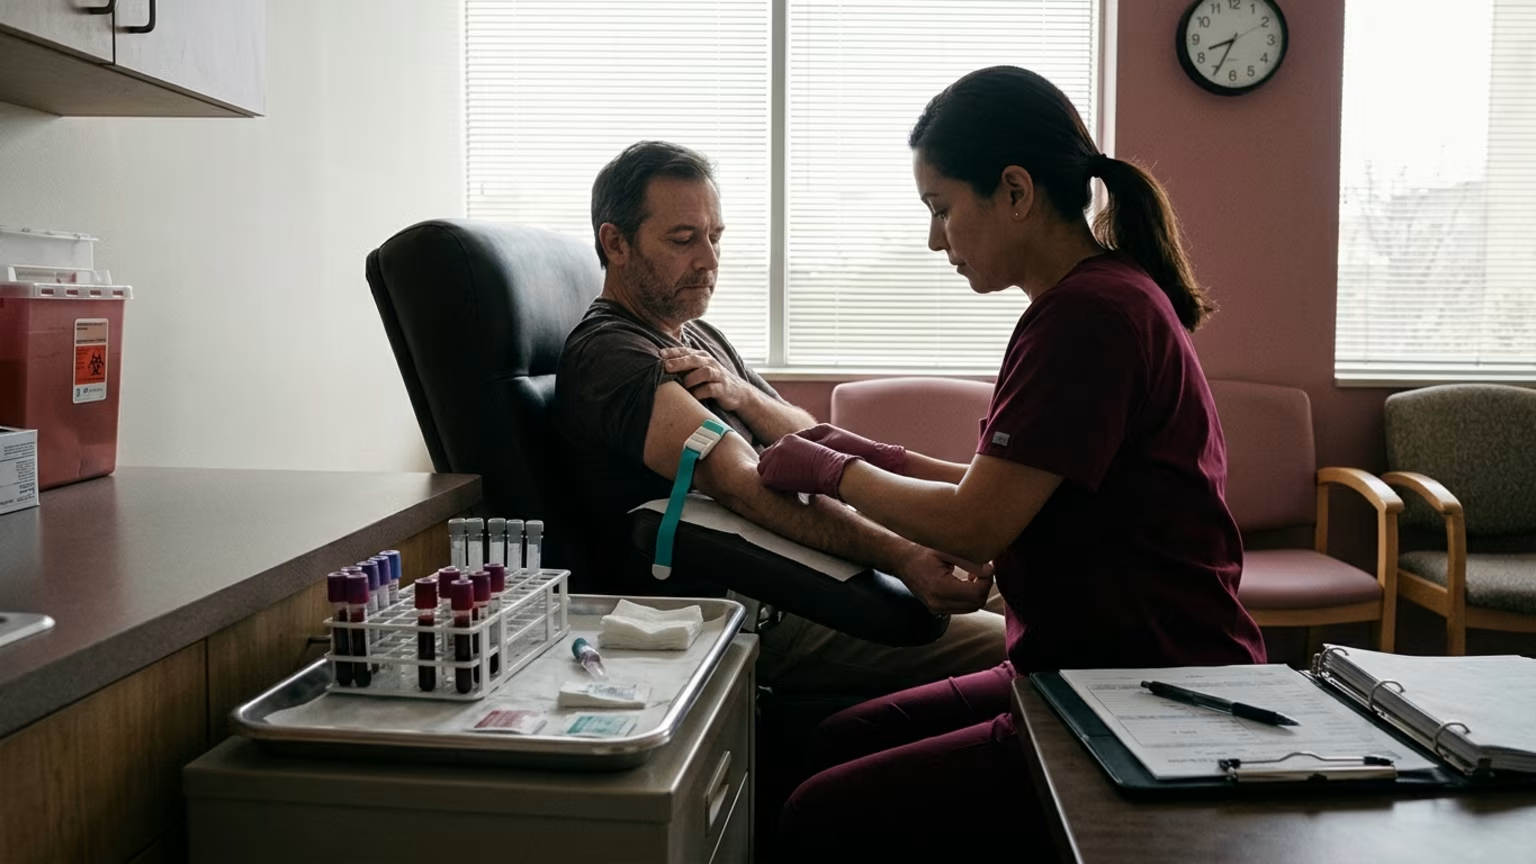
The EAU recommends testing between 07:00 and 10:00, in a fasting state and with a reliable assay. These conditions are part of its diagnostic approach rather than incidental details about the appointment.
A result should therefore be discussed alongside its collection circumstances. The useful comparison is not simply between a number and a cutoff. It is between a properly assessed measurement and the clinical question the test was intended to address.
The guideline recommends confirming a low result on at least two separate occasions before testosterone therapy. Repeated measurements address whether the laboratory finding is consistent. Assessment of symptoms and signs addresses whether it fits a clinical diagnosis.
These are separate tasks. A repeat result does not replace a symptom assessment, and a concerning symptom does not remove the need to establish the laboratory pattern.
In adult men, the EAU's framework centers on symptoms or signs compatible with testosterone deficiency alongside consistently low morning results. It does not treat the laboratory number as a substitute for understanding how the man is feeling or what a clinician finds during assessment.
This distinction matters when a man has several concerns at once. A low result may become the most noticeable item on a report, but it should not automatically become the explanation for every change in health. The clinician's task is to assess whether the symptoms and biochemical findings belong together.
For that conversation, it helps to separate two descriptions: what has changed in daily life and what the laboratory measured. Keeping those descriptions separate allows the clinician to assess their relationship rather than starting with an assumed hormone explanation.
Weight concerns and sleep problems also belong in the history. In the research discussed below, however, they are potential contributors or associated factors rather than a symptom checklist that establishes hypogonadism. Their presence is a reason to bring context to the assessment, not a reason to skip it.
The evidence supports considering several inputs, but they do not all have the same status:
Distinguishing these categories prevents an observed association from being treated as a proven personal cause. It also keeps testing conditions separate from longer-term health concerns.
An observational cohort published in the Journal of Endocrinological Investigation reported more generalized and abdominal obesity among men with below-normal testosterone. It also found lower total testosterone among men classified as overweight or obese.
The study shows an association rather than establishing its direction. It does not resolve whether weight-related changes lower testosterone, lower testosterone contributes to weight changes or other influences help explain both findings. That limitation is central to how the result should be used.
The practical value is that weight provides relevant clinical context. It is not evidence that body size alone identifies the cause of an individual man's result. Testostra's discussion of the relationship between body fat and hormone results provides related background for that conversation.
The EAU recommends weight loss and lifestyle changes as the first approach for men with hypogonadism who are overweight or obese. This is a clinical recommendation for a defined group, not a conclusion that every low testosterone result is explained by excess weight.
It also helps separate two questions that can otherwise become tangled. One is whether excess weight deserves attention within the person's care. The other is whether the man meets the clinical and laboratory criteria for hypogonadism.
Those questions can be considered together. Attention to weight does not remove the need to assess persistent symptoms and consistently low results. Equally, the presence of a low result does not make the broader health context irrelevant.
A secondary report summarizing a controlled sleep-restriction study describes 10 healthy young men who slept about five hours per night for a week. Their daytime testosterone was reported to fall during the restricted-sleep period.
Unlike the obesity cohort, this experiment changed a condition rather than simply observing a relationship. However, its small sample and young healthy participants limit how confidently the finding can be applied to older men or men with chronic illness or sleep disorders.
The practical implication is to include sleep problems in the clinical conversation. The finding should not be converted into a personal prediction about how much testosterone will change after a particular adjustment to sleep.
Weight or metabolic concerns and sleep problems are useful context to bring to an evaluation. The strongest direct guideline recommendation discussed here concerns overweight and obesity. It should not be expanded into a claim that a particular metabolic condition explains an individual's testosterone result.
Nor do the findings establish that changing weight or sleep will necessarily normalize testosterone or resolve symptoms. A guideline recommendation and a study finding inform care, but neither supplies an individual outcome in advance.
If symptoms continue or repeat measurements remain low, clinical follow-up remains important. An associated health concern should be considered alongside the findings rather than treated as a settled explanation for them.
Ask your physician: “Do my symptoms fit testosterone deficiency? Were the testing conditions appropriate and should the measurement be repeated? How should weight or sleep concerns affect the assessment? What further evaluation is appropriate if symptoms and low results persist?”
A low testosterone finding calls for interpretation by the treating clinician; Testostra addresses the reader's need to understand the report. Its biomarker reporting explains terms such as SHBG alongside total and free testosterone, helping men prepare better questions without replacing professional care.
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.





Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra