

Learn how clinicians evaluate erectile dysfunction and fertility concerns separately without jumping to immediate conclusions about low testosterone levels.





When men experience changes in their reproductive health, distinguishing an erectile function issue from a fertility concern is a critical medical decision that dictates the entire testing and treatment protocol.
The information provided in this article is for educational purposes only and does not constitute medical advice. Readers should consult a qualified clinician for personalized diagnosis and treatment.
Erectile dysfunction and reduced libido often prompt men to question their overall hormone levels. Men frequently assume that a sudden drop in physical desire points directly to a systemic hormonal failure. However, medical guidelines require a much more rigorous clinical investigation before reaching any definitive conclusions. The European Association of Urology, or EAU, recommends that clinicians screen men with erectile dysfunction for possible hypogonadism symptoms.
This initial screening specifically looks for signs like decreased libido during the first clinical assessment. A thorough evaluation always involves a detailed medical and sexual history to establish the foundational facts. During this comprehensive history gathering, the EAU asks clinicians to track specific physical markers over time. Doctors will carefully assess the rigidity and duration of both sexually stimulated and morning erections.
They will also ask patients to describe any recent changes in desire, general arousal, ejaculation, and orgasm. These specific questions provide highly valuable clinical context for the attending physician navigating the diagnosis. They help the doctor form a complete picture of the patient's current sexual health status. You can better prepare for these conversations by understanding how to evaluate testosterone and sexual health claims accurately.
While these physical clues are important, they do not form a clinical diagnosis on their own. The EAU clearly notes that erectile dysfunction can stem from vascular, hormonal, neurologic, or anatomical causes. Furthermore, psychological factors and various medication side effects can play a significant role in altering physical performance. Often, these distinct underlying causes overlap within the same patient at the exact same time.
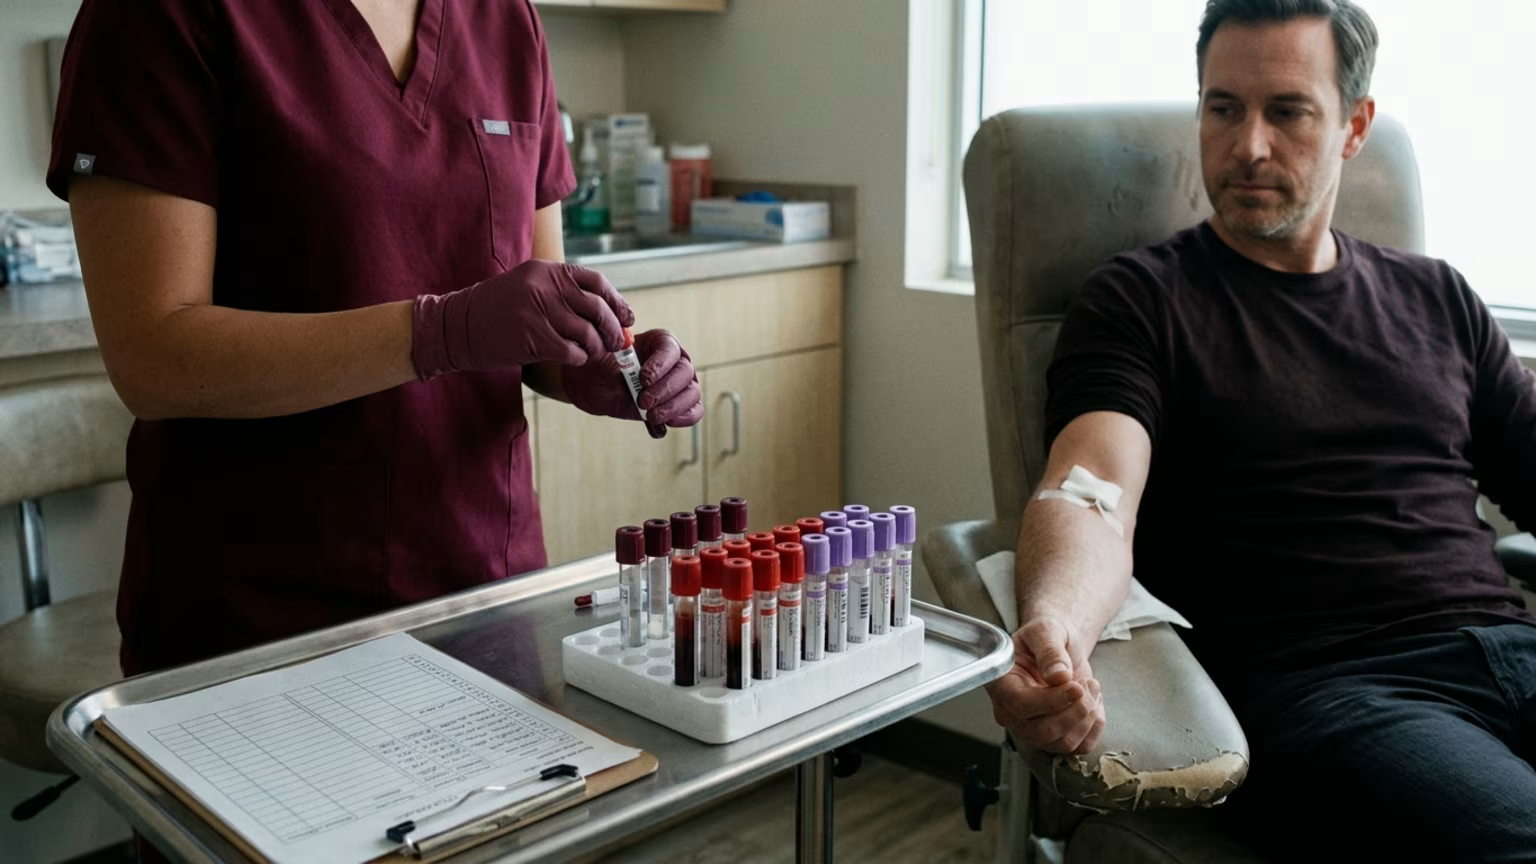
Because multiple biological systems govern sexual arousal, poor erectile function alone cannot confirm a testosterone deficiency. When a doctor suspects a true hormonal link to these symptoms, objective blood testing becomes absolutely necessary. The EAU recommends early-morning, fasting total testosterone testing as a standard part of the hormonal evaluation for erectile dysfunction. This specific test timing helps capture the hormone at its daily peak for the most accurate baseline measurement.
In certain medical situations, bioavailable or calculated free testosterone measurements may help clinicians corroborate the initial total testosterone results. These specific laboratory tests clearly separate subjective physical changes from documented, objective medical baselines. Using correct and consistent testing methods helps prevent false assumptions about your long-term hormonal health. It gives your physician the exact data required to move forward safely.
While erections and sexual desire relate to immediate physical performance, fertility involves entirely distinct biological mechanics. Medical professionals treat fertility issues as a completely separate clinical inquiry from erectile dysfunction. The EAU defines infertility as the inability of a sexually active, non-contraceptive couple to achieve spontaneous pregnancy within 12 months. This specific 12-month timeframe provides a clear benchmark for when clinical intervention becomes medically appropriate.
When a couple seeks medical help after this period, the guidelines firmly recommend evaluating both partners together. A basic semen analysis is a very common starting point for the male partner during this joint evaluation. However, the EAU cautions that a semen analysis alone cannot independently distinguish fertile from infertile men. The laboratory results might show normal parameters while a hidden mechanical or genetic issue actively prevents conception.
Therefore, the guidelines recommend a comprehensive andrological examination for infertile couples seeking clinical assistance. This highly thorough check remains necessary even when a man's semen parameters fall perfectly within standard reference values. The goal is to identify blockages, structural anomalies, or specific testicular issues that standard tests might miss. Hormone testing still plays a vital role in these fertility checks, but the required blood panel expands significantly.
For men presenting with specific sperm conditions like oligozoospermia or azoospermia, the EAU advises a targeted hormonal evaluation. This recommended clinical panel includes testing for total testosterone, follicle-stimulating hormone, and luteinizing hormone. These combined measurements help doctors assess potential testicular deficiency much more accurately than a single test could. They also allow the medical team to precisely classify the specific type of hypogonadism that might be present.
Erectile function and fertility share a general hormonal foundation within the complex male endocrine system. Despite this biological connection, medical professionals weigh these factors very differently before drawing final clinical conclusions. A man might have completely normal testosterone levels but still experience severe vascular erectile dysfunction. Conversely, a man might have verified hypogonadism but manage to maintain functional sperm parameters for a period of time.
Because of these highly complex variations, physicians rely heavily on structured interviews and validated questionnaires during assessments. These specific assessment tools help doctors cleanly isolate the exact nature of the primary medical complaint. The diagnostic path diverges immediately based on the specific physical symptom the patient actually reports. If a patient reports a persistent lack of morning erections, the doctor will look closely at vascular and hormonal indicators.
If the core complaint is a lack of conception after 12 months, the focus shifts to semen analysis and endocrine markers. Learning how symptoms, risk factors, and causes of low testosterone overlap can help you describe your situation more clearly. Total testosterone serves as a standard common denominator in both of these distinct clinical evaluation pathways. However, a single isolated laboratory result is practically never used as the sole answer for complex reproductive concerns.
The clinician must always integrate the objective blood data with the specific physical complaint reported by the patient. They must also carefully account for any external factors like cardiovascular health or current prescription drug usage. Understanding medications and testosterone interactions is vital, as many drugs can alter sexual function without actually lowering hormones. This holistic approach prevents rushed decisions based on single, isolated pieces of physical evidence.
When designing a medical treatment protocol, a patient's fertility intent acts as the most critical deciding factor. The clinical approach to managing symptomatic hypogonadism changes entirely if the patient wishes to have children in the future. The EAU explicitly states that testosterone therapy is strictly contraindicated in infertile males. It should not be used as a medical treatment for male infertility under any clinical circumstances.
This strict medical boundary forces clinicians to establish very clear long-term goals before prescribing any hormone replacement protocol. If a man has symptomatic primary or secondary hypogonadism and is not considering parenthood, the EAU supports testosterone therapy. The medical treatment is carefully reserved for managing documented hormonal deficiencies when preserving natural sperm production is no longer a priority. Patients must communicate their future family plans openly and honestly with their attending medical team.
Discussing these future plans early prevents highly inappropriate treatments that could cause severe or permanent reproductive harm. Clinicians will often thoroughly review alternative or non-hormonal treatments first if fertility remains a primary goal for the patient. For erectile dysfunction cases driven entirely by vascular or drug-related factors, resolving the underlying issue is always the preferred path. Patients reporting low libido and energy might find that lifestyle adjustments significantly improve their symptoms without requiring complex hormone therapy.
By completely separating subjective symptoms from objective test results, doctors can design safe and highly effective long-term care plans. This clinical separation ensures that men receive exactly the right treatment for their specific reproductive or sexual health concern.
Sexual function and fertility require entirely different diagnostic frameworks, but both rely on precise hormonal testing and clear patient communication to guide safe medical decisions.
When men attempt to determine the cause of their sexual health changes, they often mistake isolated symptoms for confirmed hormonal deficiencies. Testostra directly resolves this difficulty understanding total testosterone, free testosterone, SHBG and related biomarkers by detailing exact clinical assessment guidelines. We provide the objective evidence patients require to interpret physical changes alongside standard laboratory results accurately. Read Resources
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.




Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra