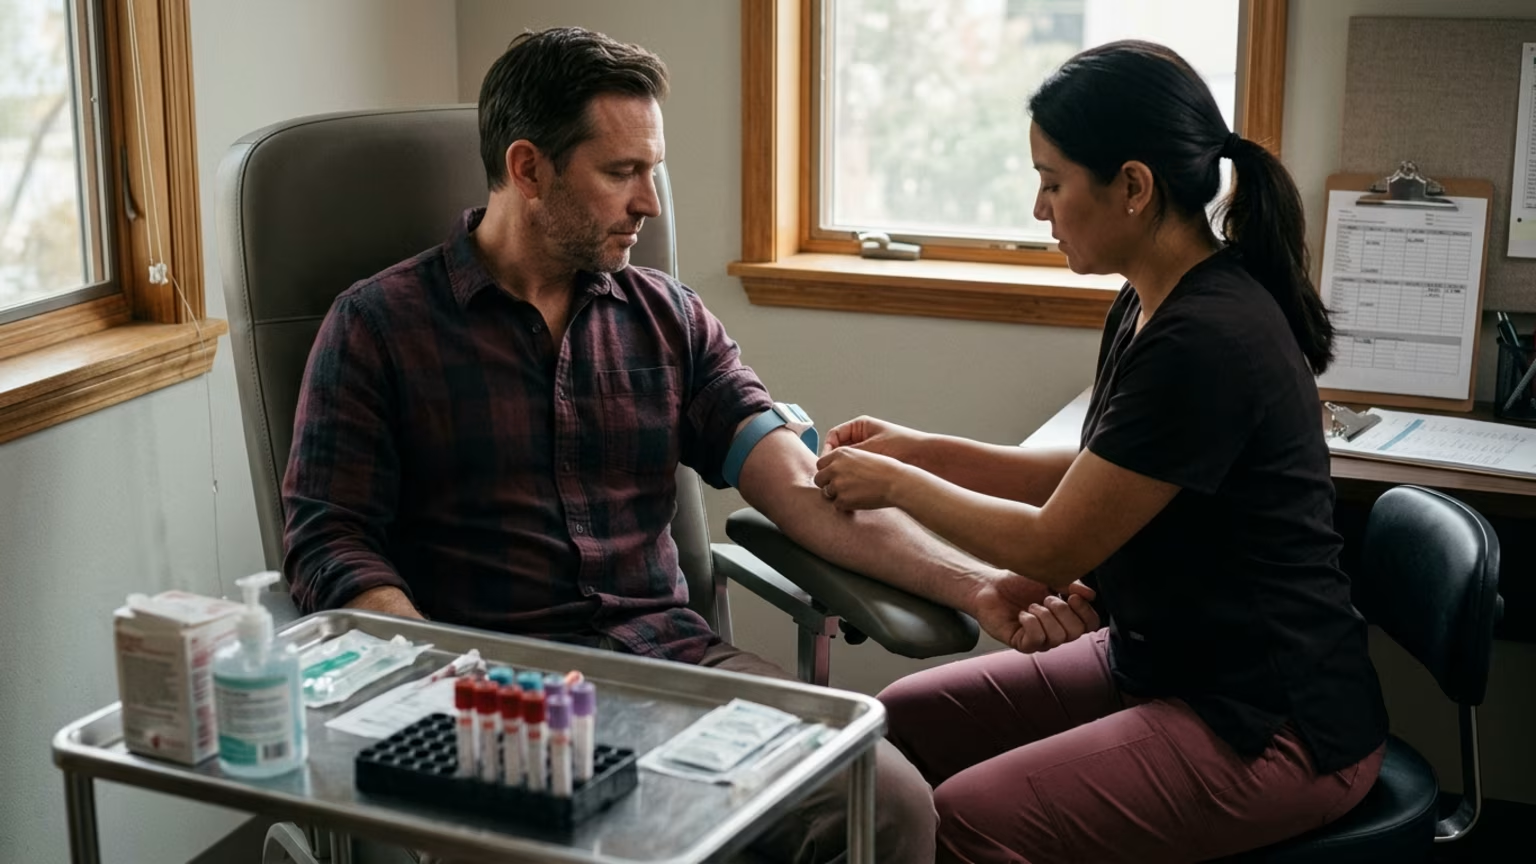

Understand fasting, timing and repeat testosterone tests, plus how clinicians review results alongside symptoms and laboratory methods.





A testosterone testing protocol helps distinguish an isolated low result from consistently low measurements and gives clinicians the context needed to assess whether symptoms or signs fit testosterone deficiency.
This article is for informational purposes only and is not medical advice; a qualified clinician should determine your testing plan and interpret your results.
The European Association of Urology (EAU) recommends fasting morning total testosterone measurements when assessing late-onset hypogonadism. Its guidance combines test results with compatible symptoms or signs rather than treating blood testing as a stand-alone diagnosis.
Before arranging the draw, ask the ordering clinician or laboratory to confirm the preparation they want. The questions below cover the conditions the EAU identifies as relevant.
The EAU guideline reports that non-fasting measurement can underestimate total testosterone by more than 30%. This is a guideline-reported finding, not a prediction that eating will change every person's result by that amount.
Preparation is about making the sample suitable for clinical review, not trying to produce a preferred number. Testostra's explanation of fasting in the testing process provides more context for that conversation.
The EAU's approach is a sequence of assessment and confirmation. The steps below describe that clinical process rather than a personal diagnostic checklist.
This assessment establishes what the laboratory testing is meant to clarify. It does not turn a symptom into proof of a hormone disorder. A discussion about symptoms alongside repeat blood testing helps explain why both parts of the assessment matter.
This is the point to raise an acute illness or an unusual sleep schedule. Ask for the actual preparation instructions so that the conditions of the draw are understood before the sample is collected.
For the later discussion, keep track of the draw time and whether the sample was fasting. Also tell the clinician about illness and your sleep schedule. These details connect the result to the circumstances in which it was obtained.
At this stage, the useful question is whether the measurement supports further evaluation under appropriate conditions. The number should not be separated from the symptoms or signs that prompted testing.
Repeating the measurement addresses the fact that one test may not represent a person's usual level. The ordering clinician should arrange the repeat and determine the appropriate conditions rather than leaving that decision to a single laboratory number.
The purpose of confirmation is not simply to collect another number. It is to establish whether the laboratory evidence and clinical picture belong together before decisions about diagnosis or therapy.
The central output in this protocol is a total testosterone value reported with its units. A clinician's review then adds the measurement method and the circumstances of collection. The laboratory number is one part of that review, not its conclusion.
The EAU guidance does not establish a universal report layout. Ask the clinician to identify the relevant values and units on your own report rather than assuming that every laboratory presents its findings in the same way.
The EAU emphasizes reliable testing and collaboration between clinicians and local laboratories. It notes that assays and pre-analytic protocols vary. That is why the method belongs in the conversation about a result, particularly when the clinician is comparing measurements.
The guideline describes LC-MS/MS as the most accurate method for sex steroid evaluation. That statement identifies a laboratory method; it is not a requirement for readers to choose their own testing platform. The clinician and laboratory can clarify which assay was used and how it fits the evaluation.
Total testosterone and free testosterone should be identified separately during the review. The EAU names equilibrium dialysis as the most accurate method for measuring free testosterone. It also describes calculation using SHBG and albumin as an alternative.
If free testosterone appears among the results, a useful question is whether it was measured or calculated. If it was calculated, ask how SHBG and albumin were used. This keeps the discussion focused on what the reported value represents rather than treating all testosterone-related results as interchangeable.
These methods do not create a patient-directed checklist of extra tests. Deciding which measurements are appropriate remains part of the clinical evaluation. Testostra's guide to the distinction between total and free measurements offers background for discussing those terms.
The EAU identifies 12 nmol/L as a reliable threshold for late-onset hypogonadism in its guidance. The same guidance requires clinical context and confirmation. A patient should not use that threshold alone to decide whether they have a hormone disorder or need treatment.
The review should connect the reported value with its units and method, then with the sampling conditions and clinical findings. A result that attracts attention on a report still needs that wider assessment. The same principle applies when comparing the first sample with the repeat.
Once the results are in hand, arrange a review with the ordering clinician. Bring the report and a short account of the conditions of each draw. Make sure the discussion includes the timing and fasting status as well as illness and sleep patterns.
Three questions can keep that appointment focused:
Leave decisions about diagnosis and treatment to qualified care. The responsible next step is a contextual review of the findings, not a conclusion based on one reading.
Confirming a low testosterone result requires consistent testing conditions and clinical judgment, while Testostra keeps its role educational. Its evidence-led articles help men understand how total testosterone, free testosterone and related biomarkers such as SHBG fit into a clinical discussion rather than treating a laboratory value as a diagnosis.
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.





Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra