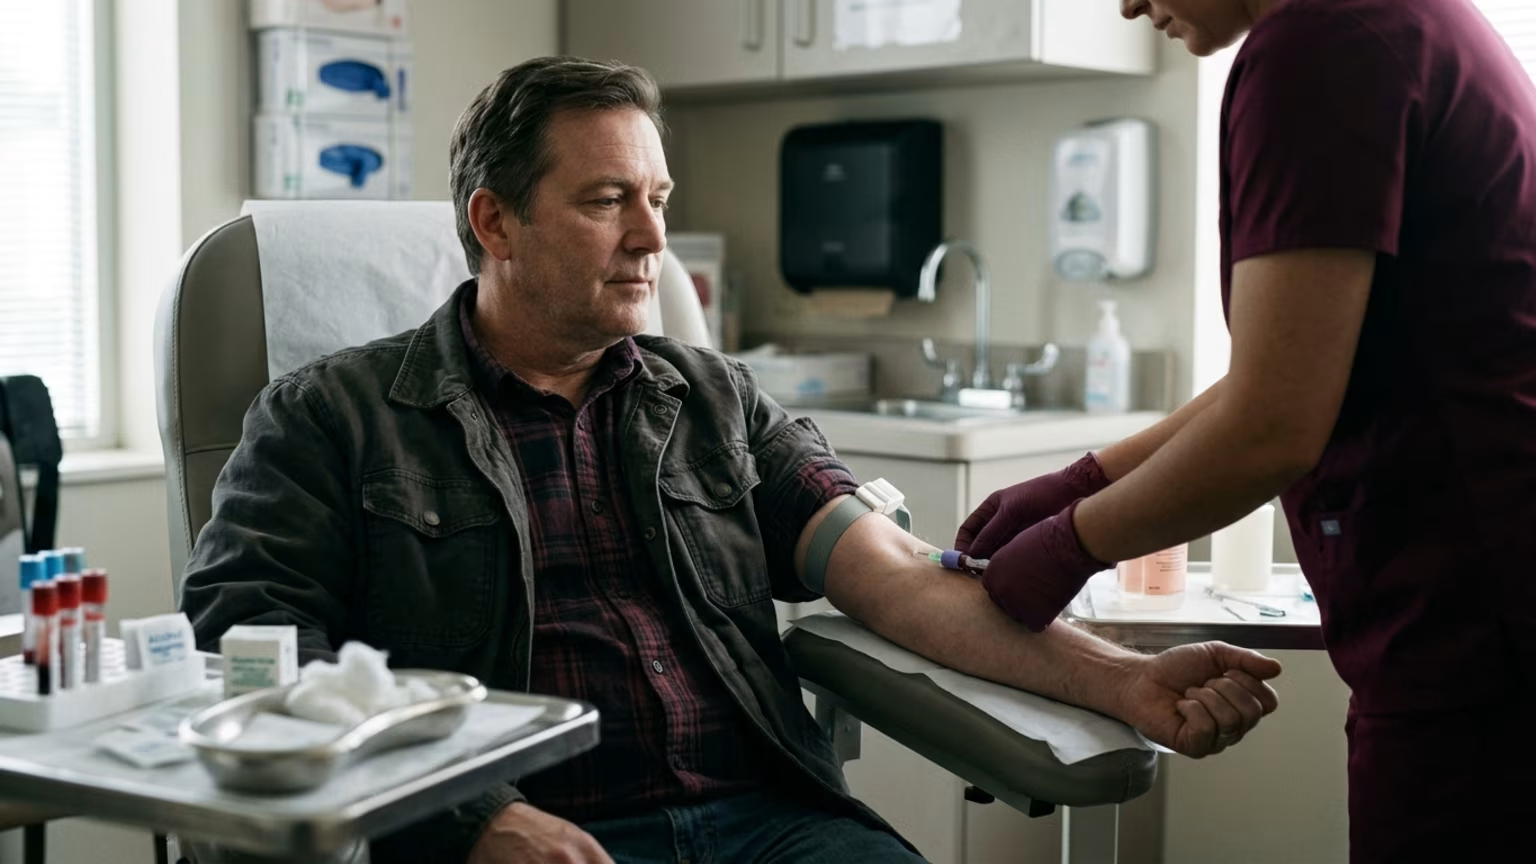

Understand how clinicians interpret testosterone tests. Learn why a diagnosis requires repeat testing, reliable assays, and compatible clinical symptoms.





The clinical evaluation of male hormones requires weighing a single initial laboratory result and subjective physical symptoms against the comprehensive diagnostic standard of repeat, fasting biochemical confirmation.
This content is provided for informational and educational purposes only and does not constitute medical advice. Readers should always consult a qualified healthcare professional for medical diagnoses and treatment decisions.
Men often notice physical changes long before they schedule a diagnostic blood test. Health information sources report that low libido, fewer spontaneous erections, fatigue, and low mood are common indicators of a potential hormone issue. When men experience these issues, they frequently assume that a deficiency is the only possible cause. However, these specific physical signs are not exclusive to male endocrine disorders. Because these symptoms frequently overlap with other medical conditions, health experts note they cannot stand alone as proof of a physical deficiency.
The central diagnostic principle requires that these compatible clinical features occur alongside objective measurements. A physician cannot base a medical intervention solely on a patient's reported fatigue or mood changes. Symptoms simply provide the necessary clinical context for interpreting subsequent laboratory results. A symptom checklist is a reason to discuss an evaluation with a qualified clinician, rather than a final verdict.
A single low testosterone measurement is equally insufficient for establishing a medical diagnosis. The human endocrine system is dynamic, and hormone secretion fluctuates predictably throughout the day. Furthermore, a person's general health status on the day of the blood draw influences the final laboratory value. For these reasons, major medical organizations warn against relying on an isolated laboratory snapshot. Temporary illnesses or acute stress can temporarily suppress natural hormone production.
If a physician relied on a single unconfirmed test, they might misdiagnose a temporary fluctuation as a permanent glandular failure. A single laboratory reading simply indicates that further investigation is warranted. Patients investigating persistent symptoms must understand that initial results are merely the first step. Clinical guidelines demand rigorous confirmation before any medical conclusions are drawn.
To account for natural physiological variability, leading medical bodies have established strict diagnostic criteria. Guidelines call for confirmation rather than reliance on a single initial reading. A physician will only diagnose a patient when compatible symptoms occur alongside testosterone levels that are unequivocally and consistently low. This rigorous, standardized approach separates true endocrine failure from transient hormonal dips.
International organizations publish specific parameters for confirming these diagnostic evaluations. A 2026 Canadian clinic guide offers insight into how these strict standards are applied in practice. This secondary report states that the 2026 European Association of Urology guideline recommends a diagnostic threshold of 12 nmol/L. Patients must evaluate their individual results against the specific clinical framework their physician utilizes.
The timing of these confirmatory tests is a critical component of the diagnostic process. According to the same Canadian clinic guide, the EAU guideline specifically recommends two fasting morning measurements. The report notes that these samples should be drawn strictly between 07:00 and 10:00. Patients who schedule their laboratory appointments outside this required window risk returning artificially low results that complicate their evaluation.
Beyond timing and diagnostic thresholds, the physical testing equipment influences the final laboratory result. Commercial summaries report that assay differences can contribute to variations in testosterone measurements across different laboratories. While some commercial sources note that studies use cross-calibration to harmonize these measurements, inconsistency remains a recognized clinical factor. This mechanical variability is exactly why testosterone results vary and why clinicians require repeat testing.
In many clinical evaluations, an initial diagnostic workup does not yield a perfectly clear outcome. A patient might present with classic symptoms, but their total testosterone results may sit near the lower limit of normal. In these borderline scenarios, looking exclusively at total hormone production can mislead a physician. The clinical interaction between total hormone production and binding globulin concentrations requires closer evaluation.
When a patient has a condition that alters their natural binding globulin levels, total measurements lose their diagnostic clarity. Elevated binding proteins can make a normal total result look sufficient even when available hormones are actually quite low. Conversely, depressed binding proteins can artificially lower total measurements without necessarily impairing physical function. To resolve these ambiguous clinical presentations, medical guidelines introduce a secondary biomarker into the evaluation process.
A secondary summary of clinical guidelines describes free testosterone testing as appropriate in these specific borderline situations. This same summary confirms this targeted evaluation is also recommended when a known condition alters a patient's binding proteins. The free fraction represents the hormones that are unbound and actively available to the body's tissues. By measuring this specific biomarker, physicians gain a more accurate picture of a patient's actual hormonal status.
However, clinical evidence summaries show this testing is not supported as a routine replacement for total measurements. Total testosterone remains the primary diagnostic tool for the vast majority of initial clinical evaluations. Free hormone evaluation is a targeted secondary step rather than a universal starting point. Patients comparing total measurements must recognize that clinical context dictates which specific biomarker is most appropriate.
The detailed rules surrounding fasting, timing, and repeat testing exist to protect patients from diagnostic errors. If a physician skips the second confirmatory test, they risk prescribing medical treatments for a temporary physiological state. By requiring multiple morning tests, clinicians rule out daily fluctuations and short-term environmental stressors. This patient protection is the core philosophy behind the rigid confirmation guidelines published by major medical bodies.
The structured approach to borderline results further enhances this diagnostic accuracy. By reserving secondary biomarker calculations for specific edge cases, physicians avoid complicating straightforward evaluations. They rely on highly standardized protocols to guide their clinical decision-making process. This systematic escalation of testing complexity ensures that each patient receives an appropriate and necessary level of medical scrutiny.
When designing a specific evaluation protocol, physicians must navigate slight reporting differences between medical organizations. Available summaries report differences among major guidelines regarding specific diagnostic thresholds and fasting requirements. A physician must choose a consistent framework and apply its specific rules to their patient's evaluation. Despite these variations in exact numbers, the foundational requirement for biochemical confirmation remains absolute.
The ultimate goal is to establish a verified, objective baseline before discussing any potential medical intervention. A strict adherence to guideline protocols ensures that physicians treat a confirmed biological deficiency rather than a temporary fluctuation. Patients must recognize that diagnostic certainty requires patience, repeated testing, and careful interpretation of multiple physiological variables. A diagnosis is only finalized when the entire clinical and biochemical picture aligns perfectly.
A reliable diagnosis depends on viewing persistent clinical symptoms and consistently low, verified laboratory results as a single integrated picture rather than isolated variables.
When men prepare to discuss their confirmed laboratory results with a physician, they need to understand the diagnostic criteria guiding their care. Testostra directly resolves confusion about what testosterone numbers mean by mapping out the exact clinical guidelines behind repeat testing protocols. We provide the structured, objective context patients require to interpret their laboratory reports accurately before entering a medical consultation. Read Resources
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.






Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra