
Understand why clinicians repeat low testosterone tests, how timing and fasting matter, and how results fit symptoms and related biomarkers.





Repeat testosterone testing helps distinguish an isolated low result from a consistently low pattern that a clinician can assess alongside compatible symptoms and signs.
This article is for informational purposes only and is not medical advice. A qualified clinician should interpret personal results and decide which testing or care is appropriate.
The European Association of Urology (EAU) guideline recommends morning testosterone measurements under fasting conditions using a reliable assay. Preparation matters because the conditions surrounding collection can affect how the result is interpreted.
The main points to clarify with the ordering clinician or laboratory are:
These details belong to the testing plan. They are not a reason to try to influence the result or to change medicines without medical advice. The aim is a measurement that the clinician can interpret in its proper setting.
The EAU describes hypogonadism as a clinical and biochemical picture. In practice, that means the evaluation brings together symptoms and signs with appropriately collected testosterone measurements.
The clinician first considers whether the reported concerns make testosterone testing appropriate. The EAU lists reduced libido and erectile dysfunction among the more specific associated symptoms. Fewer spontaneous or morning erections are also included. Fatigue and low energy appear in the guideline alongside sleep problems and concentration difficulties.
These experiences are not exclusive to low testosterone. The EAU recommends testing men who have symptoms and advises against systematic screening with questionnaires because their specificity is poor. Understanding why symptoms need laboratory context helps explain why a symptom checklist is not the endpoint of assessment.
The clinical review includes conditions that may affect testosterone production or action. The EAU also recommends considering medicines and substances that could interfere with those processes. This information helps the clinician assess the hormonal findings within the wider health picture.
A medication history is therefore part of the evaluation rather than an unrelated administrative detail. The same applies to other known medical conditions. Their relevance is assessed by the clinician rather than assumed from a testosterone value alone.
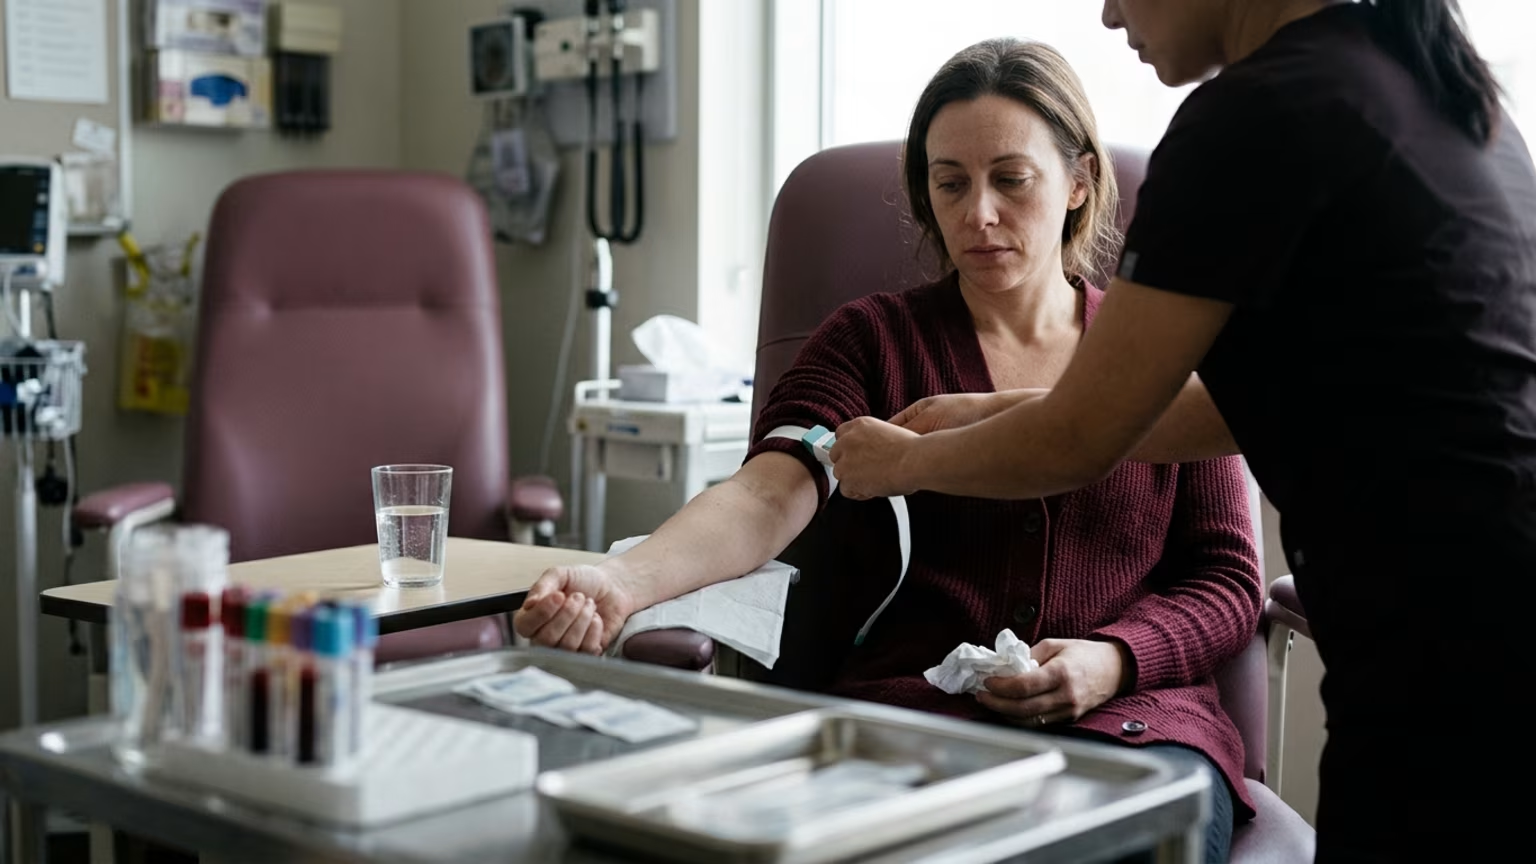
The first blood draw provides the initial biochemical measurement. EAU guidance calls for a reliable assay with collection under the timing and fasting conditions described above. An assay is the laboratory method used to measure the sample.
This measurement is considered alongside the clinical information already gathered. It records the testosterone concentration on that occasion. The next stage depends on whether the finding warrants confirmation and how it fits the rest of the assessment.
The EAU recommends confirmation after an initially abnormal result. Its diagnostic approach pairs compatible symptoms and signs with low morning testosterone on at least two occasions. A separate blood draw helps assess whether the low finding is reproducible.
This is why a clinician may recommend another test rather than draw an immediate conclusion from the first report. The practical purpose of confirming an initial low measurement is to establish whether the biochemical pattern is consistent under appropriate collection conditions.
Once the measurements have been reviewed, the clinician considers whether additional assessment is indicated. EAU guidance includes LH and FSH to help distinguish types of hypogonadism. It also includes prolactin testing in specified circumstances and SHBG assessment with free-testosterone calculation when relevant.
These tests have different roles within the workup. The guideline does not present every biomarker as a mandatory addition for every man. Selection follows the clinical findings and the question the clinician is trying to answer.
The total testosterone output is a numerical concentration expressed with a unit of measurement. The EAU gives 12 nmol/L (3.5 ng/mL) as a threshold it considers reliable for late-onset hypogonadism. It also calls for at least two separate measurements when total testosterone is below 12 nmol/L.
That threshold belongs within the guideline’s clinical framework. It is interpreted alongside symptoms and signs rather than used as a universal stand-alone diagnosis. Reading the unit is also important because the guideline expresses the same threshold in different units.
For a patient reading the report, the useful distinction is between the laboratory measurement and the medical conclusion. The report supplies biochemical information. The clinician integrates that information with the history and the testing conditions.
Testostra’s explanation of testosterone values in their laboratory context provides related background for that discussion.
The clinician then considers the results together. Low measurements obtained under appropriate conditions can support a diagnosis when compatible symptoms or signs are also present. The clinical assessment remains part of that conclusion.
When the measurements differ, they do not establish consistently low testosterone. The clinician reviews the disagreement in context rather than treating whichever result seems more concerning as decisive. Collection timing and fasting status are relevant parts of that review.
A useful way to understand this stage is that the review has several distinct components:
These are questions for the clinician’s assessment. They are not a scoring system that a patient can use to assign a diagnosis.
According to the EAU, LH and FSH help distinguish types of hypogonadism. Prolactin is considered in specified circumstances. These recommendations show why the workup may continue beyond repeating total testosterone.
SHBG and free testosterone address another part of the evaluation. Where SHBG may be altered, the guideline recommends considering SHBG measurement and free-testosterone calculation. A clinician therefore decides whether total testosterone needs this additional context.
This does not mean a longer hormone panel is automatically more useful. The relevant question is what each additional measurement contributes to the assessment. The EAU’s approach connects further testing to clinical indications rather than treating all biomarkers as interchangeable.
Repeat testing has a defined limit: it helps assess consistency. It does not identify the cause by itself or establish that a particular symptom is caused by testosterone. It also does not determine whether testosterone therapy is appropriate.
The EAU calls for assessment of possible causes and contraindications as part of the broader evaluation. It states that confirmation should precede testosterone therapy. This makes confirmation one stage of the process rather than the final treatment decision.
Fertility intentions also matter in that discussion. The guideline notes that testosterone therapy suppresses spermatogenesis, meaning sperm production. A conversation about treatment therefore involves questions that a repeat total testosterone result alone cannot answer.
Arrange a review with the clinician responsible for the testing. Have the separate reports available and explain any relevant differences in collection conditions. Bring an accurate account of symptoms and current medicines so the discussion includes more than the numbers.
Useful questions include:
The responsible next step is a clinical interpretation of the complete picture. Treatment decisions belong after that review rather than being inferred from an isolated result.
Repeat measurements address consistency rather than every question about a hormone panel, a distinction that shapes Testostra’s evidence-led explanations. For men uncertain about total testosterone, free testosterone and SHBG, its biomarker coverage supplies plain-language context for medical conversations while keeping education separate from individual diagnosis or treatment.
Testostra follows testosterone research, clinical guidance and emerging evidence without turning general information into personal treatment advice.



Send us a question, research idea or topic suggestion. Reader questions help shape future Testostra content.
Contact Testostra